Domain A · Neurobiology & neurology
Brains, maps, and lesions
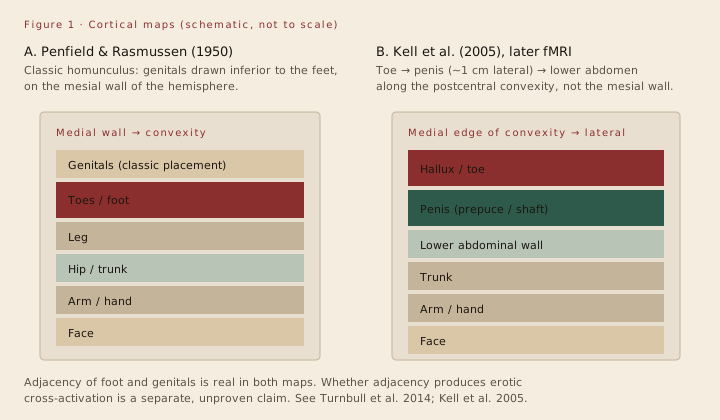
The most famous answer to “why feet?” is a drawing. Penfield’s homunculus places genitals beside the feet. Ramachandran guessed that spillover from that adjacency eroticizes the foot. The guess is elegant, contested, and not a finding.
Somatosensory adjacency hypothesis
E3- Mechanism
- Because foot and genital representations are neighbors in primary somatosensory cortex (S1), residual cross-talk or developmental ‘smearing’ could couple genital arousal to foot percepts, and, by a further leap, to the sight of feet.
- Sources
- Penfield & Rasmussen, The Cerebral Cortex of Man (1950). Ramachandran & Blakeslee, Phantoms in the Brain (1998). Popular formulation: “the foot region of the cortex is right next to the genital area.”
- Critique
- Turnbull, Lovett, Chaldecott & Lucas (2014, Cortex 53: 146-154, doi:10.1016/j.cortex.2013.07.010): in ~800 raters, feet were among the least erogenous body parts; S1-neighbor correlations failed; S1 stimulation is not erotogenic in the classical literature. Fetish desire is often visual and object-mediated (shoes), which S1 adjacency does not predict.
- Open questions
- Does any imaging protocol show above-chance S1 co-activation of foot and genital fields during erotic foot stimuli in people with primary podophilia versus controls?
- Cross-links
- A2, A3, C1, E1. Best candidate for specificity if it were true; presently unproven.
Ramachandran’s 1993/1998 clinical remarks are the origin of the public story, not a test of it. Treat the adjacency claim as E3 theory plus E2 anecdotes, never as replicated neuroscience of fetishism.
Phantom-limb remapping as natural experiment
E2- Mechanism
- After lower-limb amputation, vacated foot cortex is invaded by neighboring inputs. Genital stimulation may then be felt in a phantom foot; some patients report erotic sensation referred there.
- Sources
- Ramachandran, D. O. Hebb lecture, “The perception of phantom limbs” (1998, Brain 121: 1603-1630): two patients reported phantom-foot sensations during intercourse; one engineer described a spatially enlarged orgasm. Aglioti, Cortese & Franchini (1994) mapped referred sensations from genitals in lower-limb amputees more systematically.
- Critique
- Deafferentation plasticity is not the intact-brain condition of most fetishists. N is small. Referral of sensation ≠ erotic preference for other people’s feet as visual objects.
- Open questions
- What is the incidence of referred genital-to-phantom-foot sensation in consecutive lower-limb amputees, with pre-amputation sexual history recorded?
- Cross-links
- A1, A3.
Where the genitals actually sit
E2- Mechanism
- If Penfield misplaced the genitals, the adjacency story changes shape. It does not disappear: later maps still put genitals beside the foot/leg sequence, on the convexity rather than the mesial wall.
- Sources
- Kell, von Kriegstein, Rösler, Kleinschmidt & Laufs (2005, J Neurosci 25: 5984-5987, doi:10.1523/JNEUROSCI.0712-05.2005): fMRI in 8 men, toothbrush stimulation, penis ~1 cm lateral to hallux. Cazala, Vienney & Stoléru (2015, Socioaffective Neuroscience & Psychology) review mixed EEG/MEG vs fMRI placements. Knop et al. (2022, J Neurosci) map the female clitoris onto dorsolateral postcentral gyrus, adjacent to hips/legs.
- Critique
- Map revision is about somatotopy, not fetishism. Closeness remains; mechanism remains unshown. Spatial resolution of group fMRI is coarse relative to the millimetre story being told in popular summaries.
- Open questions
- A high-resolution, pre-registered comparison of foot-genital overlap in people with versus without podophilia.
- Cross-links
- A1, A2, Turnbull 2014.
Temporal lobe epilepsy and Klüver-Bucy-type hypersexuality
E2- Mechanism
- Bilateral temporal (especially amygdala-related) disruption can disinhibit sexual behaviour. Ictal or post-ictal sexual automatisms, interictal hyposexuality, and rare postoperative hypersexuality are described. A handful of case reports link temporal dysfunction to new paraphilic foci.
- Sources
- Klüver & Bucy (1939), animal syndrome. Terzian & Dalle Ore (1955), human analogue. Blumer (1970, Am J Psychiatry): among 50 TLE patients, hyposexuality was common; 7 had hypersexual episodes, often after seizure cessation. Baird, Wilson, Bladin, Saling & Reutens (2002, Epilepsy & Behavior): 7 cases of postoperative hypersexuality, often with contralateral temporal abnormality and psychosocial stress. Baird, Wilson & Reutens (2007, J Neurol Neurosurg Psychiatry review) tally a small set of paraphilia-with-temporal-dysfunction reports.
- Critique
- These are lesion and epilepsy stories. They show that sexual targeting is biologically labile. They do not pick out feet. Hypersexuality is usually nonspecific. Forensic and ethical complications (including rare illegal behaviour after surgery) belong to clinical management, not to ordinary podophilia.
- Open questions
- Is there any consecutive TLE series in which foot-focused interest appears above base rate?
- Cross-links
- A5, G3.
Dopamine-agonist paraphilia in Parkinson disease
E2- Mechanism
- D2/D3-preferring agonists (pramipexole, ropinirole, pergolide, etc.) can produce impulse-control disorders, including hypersexuality and, in case reports, novel paraphilic behaviours. Dose reduction often attenuates the urges.
- Sources
- Klos, Bower, Josephs, Matsumoto & Ahlskog (2005, Parkinsonism Relat Disord). Solla, Bortolato, Cannas, Mulas & Marrosu (2015, J Neurol Sci / PMC review): 22 papers, 31 PD patients, almost all male, high levodopa-equivalent doses, frequent comorbidity with other ICDs.
- Critique
- Iatrogenic disinhibition in a neurodegenerative illness is not a model of developmental fetishism. Foot is not singled out. All-male case series reflects both PD demographics and reporting bias.
- Open questions
- Prospective ICD monitoring that records stimulus class, not only ‘hypersexuality’ as a lump.
- Cross-links
- A4, B2 (reward), C1.
Peripheral sensory properties of the foot
E3- Mechanism
- The foot is said to be ticklish, densely innervated, odoriferous, and intimate because it is usually covered. Those properties would make it a salient CS.
- Sources
- Textbook two-point discrimination: the sole is sensitive, the dorsum less so; the fingertips are more densely innervated than the foot. Ellis (1906/1927) already noted that the hand is less often a fetish than the foot, which undercuts a pure-density story.
- Critique
- What is measured (mechanoreceptor maps) is not what is asserted (therefore erotic). Tickle is near-universal; podophilia is not. Odor matters for some people (see A8) and is irrelevant to clean-foot visualists.
- Open questions
- A within-subject study of tactile thresholds, odor ratings, and erotic ratings of feet versus hands in people with and without the interest.
- Cross-links
- A8, B3, D3, D4.
Genetics and familial data
E2- Mechanism
- No ‘foot fetish gene’ is known. A weak claim: some general liability to atypical sexual learning or to paraphilic clustering might be familial.
- Sources
- Gorman (1964, Br J Psychiatry 110: 255-256): fetishism in identical twins, a two-page case. Labelle, Bourget, Bradford, Alda & Tessier (2012, ISRN Psychiatry): five selected families with mixed paraphilias across generations; no simple Mendelian pattern. Alanko, Salo, Mokros & Santtila and related Finnish twin papers address other paraphilic interests (e.g. sexual interest in youth, 2013), not podophilia. Comings (1994) reported correlations between putative TS genetic loading and a menu of sexual items including fetishism; the TS-gene framing is historically controversial and not a podophilia study.
- Critique
- There is no adequate heritability estimate for foot fetishism. Absence of studies is a gap, not a negative finding of zero heritability.
- Open questions
- A classical twin design with a specific foot-interest item, not a bundled ‘fetishism’ item.
- Cross-links
- B5, C5.
Olfactory component (historical)
E4- Mechanism
- Freud’s 1910 footnote to the Three Essays tied foot and hair fetishes to repressed coprophilic smell-pleasure: the foot as a once-odorous object, later idealized. Some community subtypes are explicitly olfactory.
- Sources
- Freud 1905, footnote added 1910; returned to in the Rat Man analysis and in Civilization and its Discontents (1930) on organic repression of smell.
- Critique
- Unfalsified, species-wide story. Many foot fetishists deny odor as a cue; many odor-sensitive people have no fetish. Subtype, not essence.
- Open questions
- What fraction of people with podophilia name odor as necessary, enhancing, or irrelevant? Unknown in a representative sample.
- Cross-links
- A6, B7, H1.
Confidence, Domain A
Solid: somatosensory maps exist; foot and genitals are neighbors on current maps; amputation can remap referred sensation; dopaminergic drugs and temporal lesions can disinhibit sexuality. Contested: S1 as the erotic map (Turnbull 2014 is the paper to beat). Unknown: any neural signature of podophilia itself. No category in this domain currently explains specificity at E1.